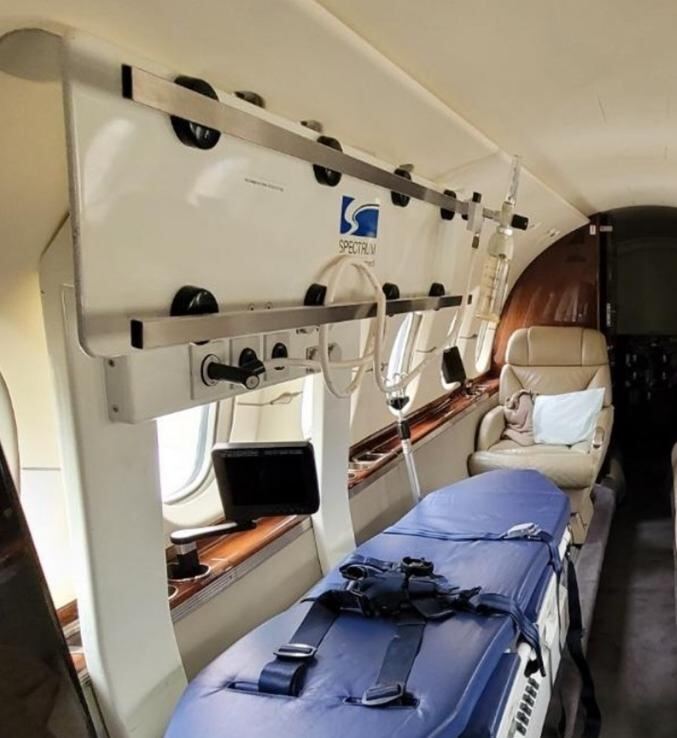
Medevac Bali: Air Ambulance & Tourist Repatriation
Bali carries one of the region's heaviest tourist medevac loads. ICU-grade air ambulance and insurer-driven repatriation from Denpasar, configured against the clinical picture.
Speaking to someone is usually the fastest way to start.
Our medical transfer desk is staffed 24 hours. You do not need complete information to make the first call, the current location of the patient and where they need to go is enough to begin.
Patient information is treated as sensitive. Medical detail and uploaded reports go only to the clinical and operations coordinators handling the case, are never placed in web addresses, and are never shared with advertising or analytics platforms.
Medevac from Bali, built around tourist repatriation
Bali (Denpasar DPS/WADD) generates sustained demand for medical evacuation, driven by a large visitor population and the limits of local definitive care for serious cases. Aviall arranges fixed-wing air ambulance and repatriation from Bali to Australia, Singapore and home countries, working to the clinical picture rather than a fixed aircraft type.
Every mission is owned by a single coordinator on a 24/7 desk, with clinical teams, aircraft sourcing, ground ambulance staging and cross-border clearances managed door-to-door.
When to call for a Bali medevac
Bali demand is dominated by visitor incidents and insurer-driven repatriation, alongside resident transfer to definitive care.
Tourist repatriation to Australia, Singapore or home country after illness or injury
ICU-grade transfer with ventilator, infusion pumps, monitoring and clinical escort
Diving and marine incident response with appropriate cabin-altitude management
Road-trauma and neurosurgical cases requiring definitive care offshore
Neonatal and paediatric transfer with isolette-compatible loading
Insurer- and assistance-company-driven cross-border cases
Aircraft and clinical configurations from Bali
The airframe is matched to range, runway and clinical fit-out. The common Bali-to-Australia and Bali-to-Singapore sectors shape selection.
Midsize jet, extended-range ICU fit-out for repatriation to Australia and Singapore
Long-range jet, onward international repatriation with ventilator support
Light jet, shorter regional sectors and single-stretcher missions
Commercial wide-body stretcher where airline approvals and timing allow
Turboprop for connecting retrieval within the Indonesian archipelago
Coordination model from Bali
A named coordinator carries the case to bed-to-bed handover, with continuous flight-following and a written record at each clinical interface.
24/7 medical activation desk on a single number
Clinical lead in contact with the sending and receiving teams
Ground ambulance staged at origin and destination
Customs, immigration and diplomatic clearances on cross-border missions
MEDIF, oxygen calculations and airline approvals where commercial uplift is used
Insurers, assistance companies and families all deal with the same coordinator
Bali network, related pages
Where a transfer sits alongside group or freight movement:
Repatriation to Australia, Singapore or home country with insurer coordination.
ICU air ambulance
Ventilator, pumps and monitoring fitted to the patient's acuity, with escort to match.
Diving incident response
Cabin-altitude management appropriate to decompression cases.
Trauma transfer
Road-trauma and neurosurgical cases moved to definitive care offshore.
Neonatal & paediatric
Isolette fit is confirmed against the aircraft door and cabin before we commit, with a specialist retrieval team tasked.
Single coordinator
One person owns the case end to end, and you have their direct number.
Medical transfer & repatriation desk
Request a medical transfer
You do not need a complete clinical picture to contact us. Tell us where the patient is and where they need to go, and a coordinator will start assessing options, aircraft, clinical configuration, crewing, clearances and ground ambulance, while the rest of the information is still being gathered.
Enough to start
Where the patient is now
City or country, and the facility type if you know it
Where they need to go
City, country, or receiving hospital if already arranged
Rough timing
Today, within 24 hours, or later this week
How they are travelling
Seated, wheelchair, stretcher, or intensive care, an estimate is fine
Helpful, but can follow
A medical report, discharge summary or fit-to-fly assessment, uploaded securely
Treating team or transfer-desk contact, so our clinical coordinator can speak with them directly
Insurer, assistance company or funding arrangement, if one applies
Receiving hospital acceptance, where that is still being organised
Clinical acceptance and aircraft availability are confirmed after review by the clinical team and the receiving facility. Contacting us does not by itself confirm a flight, a crew or acceptance of the patient.
Privacy: patient details and uploaded reports are handled as sensitive information, stored in restricted storage, and passed only to the coordinators and clinicians working the case. They are never written into web addresses, advertising platforms or analytics events.
Urgent charter? Our ops desk is staffed 24/7.
Aircraft options within the hour and a written quote with an indicative wheels-up window.
Representative mission profiles drawn from recurring work. Identifying details, operators, hospitals, routes, aircraft tail numbers, are intentionally omitted.
International · Repatriation
Long-range stretcher repatriation across the Pacific
A complex case with ventilator and infusion support required movement from a regional Pacific facility back to a domestic tertiary centre. Aviall configured a long-range jet with a critical-care medical fit-out, coordinated bed-to-bed handover with both treating teams, and managed customs and immigration at each stop.
Outcome
Bed-to-bed transfer completed without clinical deterioration en route.
Neonatal · Critical
Neonatal transfer to a tertiary paediatric centre
A neonate requiring escalated care had to be moved from a regional hospital to a metropolitan paediatric tertiary centre. Aviall coordinated an aeromedical aircraft and a specialist retrieval team, with isolette-compatible loading and parent transit on the same airframe.
Outcome
Patient delivered to receiving NICU within the clinical window agreed by both teams.
Remote · Mining medevac
Trauma extraction from a remote mine site
An incident at a remote mine site required immediate movement of a trauma patient to a metropolitan trauma centre. Aviall launched on the standing medevac protocol, with a clinical team mobilised in parallel and the receiving trauma team pre-briefed before take-off.
Outcome
Patient on the operating table at the receiving centre well inside the planned window.
24/7 medical desk; first-call response within minutes
Aircraft sourcing
Light jet to long-range, plus turboprop for archipelago retrieval
Clinical capability
ICU, neonatal, paediatric, bariatric on request
Cross-border
Australia, Singapore and onward, clearances managed
Reporting
Insurer- and assistance-company-ready documentation
Frequently asked questions
Yes. Tourist repatriation to Australia, Singapore or home country is the most common Bali mission. Aviall works directly with insurers and assistance companies on documentation and onward coordination.
Single point of clinical accountability from the call to bed-to-bed handover. Our retrieval team had everything they needed before wheels-up.
Aeromedical retrieval lead · Tertiary hospital network
The case management discipline matched our internal standards. That is unusual in the assistance market.
Operations director · International medical assistance company
Aircraft selection was driven by the patient's clinical picture, not by what was on the apron. That is the right way around.
Critical-care physician · Repatriation case
Need a medevac flight from Bali?
Tell us where the patient is and where they need to go, that is enough to start. Our medical desk is staffed 24 hours. Attach an existing RFQ, packing list or photos straight from your phone, partial detail is enough to start.